What is nummular eczema?
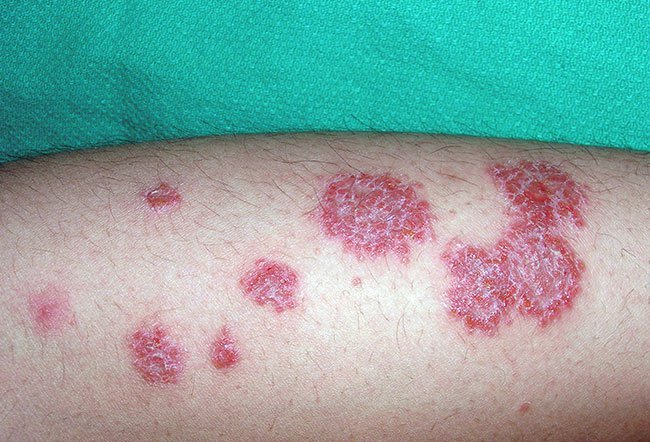
Nummular eczema is a common type of eczema defined by scattered, well-defined, coin-shaped and coin-sized plaques of inflamed skin (DermNet). It is also called discoid eczema and nummular dermatitis; "nummular" comes from the Latin word for a coin and "discoid" means disc-shaped (DermNet, BAD). The patches are itchy, swollen and cracked, and without treatment the condition can last for weeks, months or even years and keeps coming back, often in the same place (NHS).
The words eczema and dermatitis are used interchangeably for this group of itchy, inflammatory skin conditions (DermNet). Nummular eczema is one of several types, alongside atopic, contact, seborrhoeic and venous eczema (NHS, NEA).
Is nummular eczema contagious, and does it spread?
No. You cannot catch nummular eczema from someone else or give it to anyone (AAD, NEA). It is not passed on by touching the patches or sharing towels or bedding, because it is not an infection: although the bacterium Staphylococcus aureus is sometimes found on the patches and a skin infection can trigger a flare (DermNet), the eczema itself is an inflammatory reaction of your own skin and is not passed from person to person (AAD). The condition itself is not inherited either (BAD), although people with a personal or family history of atopic eczema, hay fever or asthma are more likely to develop it (AAD, MedlinePlus).
"Spreading" on your own body is a different matter. Each patch starts as a group of small spots that quickly join up into a larger patch (NHS), new patches can appear while older ones clear (AAD), and in severe cases numerous small and large itchy plaques can appear all over the body through a reaction called autoeczematisation (DermNet). This is the skin's own inflammatory response, not an infection travelling across the skin.
Who gets nummular eczema?
- Any age, but it is slightly more common in older adult men and in younger adult women (DermNet); women most often develop it before 30 and men after 50 (AAD, NEA).
- Children rarely develop it; a few children with severe atopic eczema do, and the extreme dryness of their skin may play a role (AAD).
- People with very dry skin, atopic eczema, contact dermatitis or poor circulation in the legs with venous (stasis) eczema have a higher risk (AAD, NEA).
- In men there is an association with heavy alcohol use (DermNet, AAD).
Causes and triggers
The cause of nummular eczema is not known (DermNet, NHS). What is well established is that it develops on skin that is extremely dry: very dry skin cannot provide an effective barrier, so a previously harmless substance such as soap can irritate it (NHS), and studies of the condition indicate that affected people either already had very dry skin or something had recently dried it out (AAD). Some cases are associated with colonisation of the skin by the bacterium Staphylococcus aureus (DermNet).
Flare-ups are typically set off by a trigger (AAD). The ones reported most often are:
- a local injury to the skin such as a scratch, an insect bite, a scrape or a burn (DermNet, NHS, AAD);
- a skin infection such as impetigo or an infected wound (DermNet, AAD);
- contact dermatitis: patch testing in chronic cases commonly shows allergy to metals such as nickel, cobalt and chromate (DermNet, AAD);
- dry air in winter, the heating season and cold, dry climates make it worse, and sunny or humid weather may improve it (NHS, NEA); overheating and sweating in hot, humid conditions can nevertheless set off a flare (AAD);
- intense stress (AAD, MedlinePlus);
- heavy drinking (AAD);
- varicose veins and venous eczema of the lower legs (DermNet);
- medicines that dry the skin, for example some water tablets (diuretics), some cholesterol-lowering tablets and some hepatitis C treatments (DermNet, AAD). Do not stop a prescribed medicine without talking to the doctor who prescribed it (NHS).
Symptoms: what nummular eczema looks like
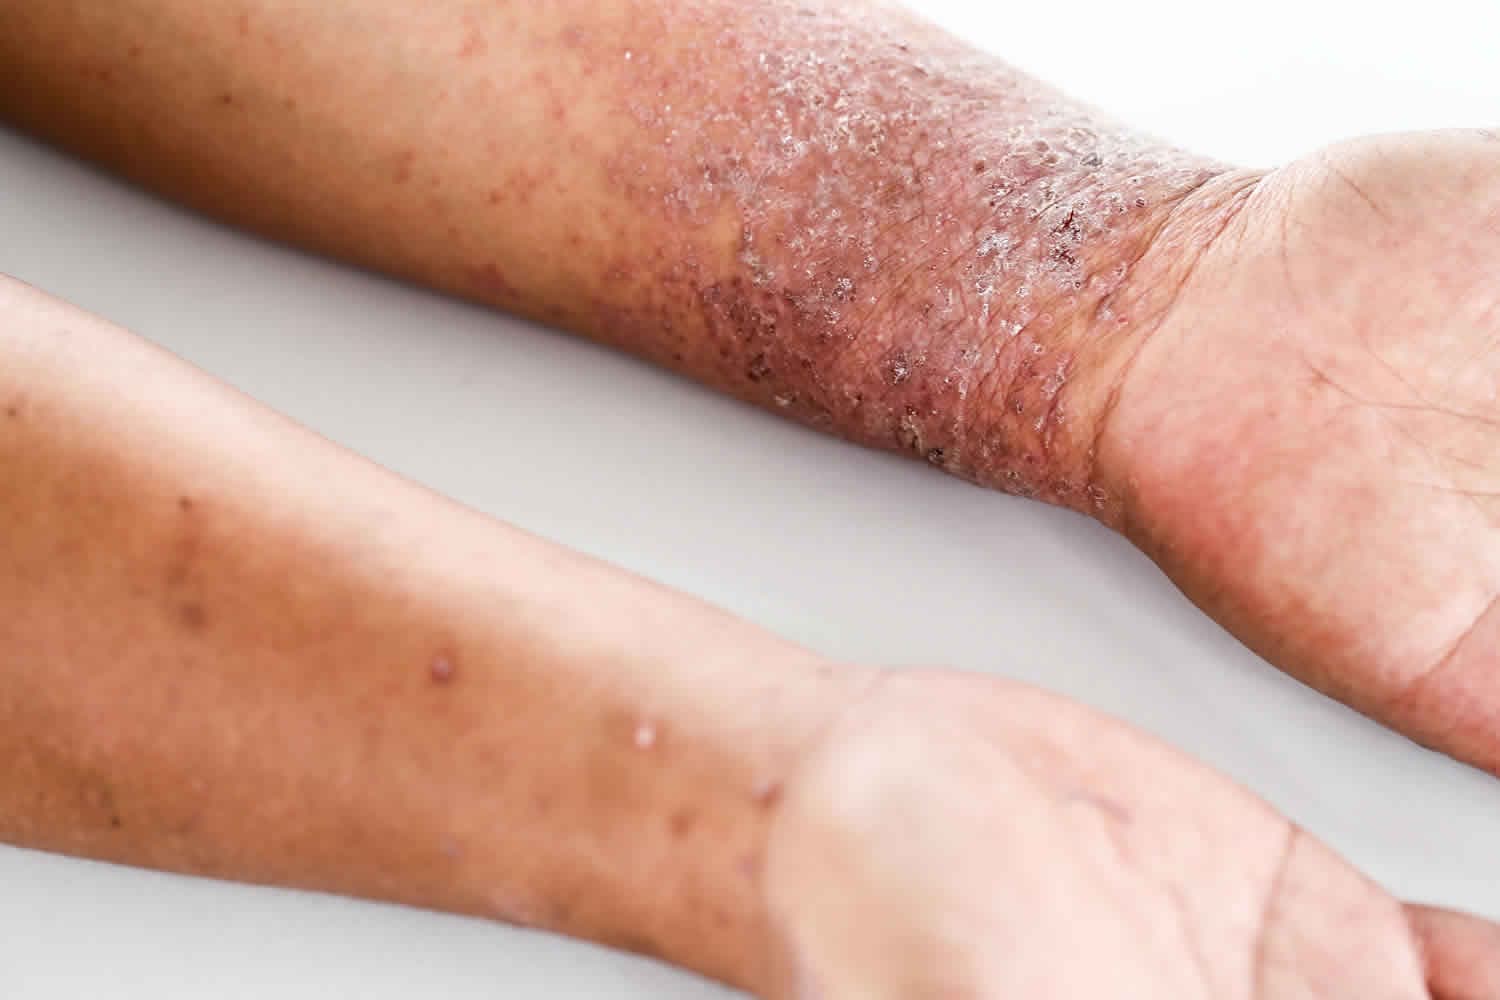
The first sign is usually a group of small spots or bumps, sometimes blister-like, which quickly join up to form larger patches ranging from a few millimetres to several centimetres across (NHS); most are 1 to 3 cm in diameter (DermNet). The patches are round or oval (DermNet) and slightly raised (AAD). On lighter skin they are pink or red; on darker skin they can be dark brown or paler than the surrounding skin (NHS).
There are two clinical forms: an exudative, acute form with oozy spots, blisters and weeping plaques, and a dry form with red, dry, scaly plaques (DermNet). Early patches are often swollen, blistered and oozing; over time they become dry, crusty, cracked and flaky (NHS). The itch is usually intense, worst at night and when you relax or try to sleep, and some people describe burning or stinging (NHS, AAD). The skin between the patches is usually dry and irritable (DermNet).
Where it appears: usually on the limbs, particularly the legs, and often on both sides, though the pattern can be asymmetrical when varicose veins are involved (DermNet); the forearms and the backs of the hands are the other common sites (AAD). The rash may be widespread (DermNet). It does not usually affect the face or scalp (NHS), so a round, scaly patch on the face is less likely to be nummular eczema and should be examined, because several other conditions, such as ringworm and psoriasis, can look similar (AAD, NEA).
As the patches clear they flatten, often from the centre first, which can leave a ring of discoloured skin that is easily mistaken for ringworm (NHS, AAD). Patches may clear without leaving any sign (DermNet). A flat darker or paler mark may remain for months, particularly in darker skin, and occasionally an area stays permanently discoloured (DermNet, NHS).
How long does it last, and does it go away?
Nummular eczema rarely clears without treatment (AAD). Untreated, it can last weeks, months or even years and may keep coming back, often in the same area as before (NHS). With early and proper treatment a patch can heal within 3 to 4 weeks (AAD, NEA). The condition tends to be chronic and often relapses, especially in cold winter months, but with treatment many cases do eventually settle for good (DermNet). Treatments control the condition rather than cure it: they can put it into remission, and it can return, particularly if treatment is stopped too soon (BAD).
Is nummular eczema dangerous?
When it is managed, nummular eczema is not a serious or life-threatening condition, although flare-ups can be uncomfortable and disrupt daily life (NEA). The problems to watch for are:
- Bacterial infection. Scratching opens the skin, and patches can become infected: signs are patches that ooze a lot of fluid, a yellow or golden crust, skin around the patches that is hot, swollen, tender or painful, feeling hot, cold or shivery, or feeling unwell (NHS, AAD). Infection needs prompt treatment (NHS).
- Eczema herpeticum. Any eczema can become infected with the cold-sore virus: clusters of itchy, painful, uniform blisters or punched-out sores that spread over days, with fever and swollen glands. It needs same-day medical care because it can affect the eyes and other organs and, rarely, can be fatal (DermNet).
- Widespread eczema. Severe nummular eczema can generalise, with itchy plaques over the whole body (DermNet).
- Discolouration. Dark or pale marks that persist for months in darker skin, and occasionally permanent discolouration (DermNet, NHS).
Nummular eczema or something else? Conditions that look similar
Round scaly patches have many causes. Ringworm and psoriasis are the two most often confused with nummular eczema (AAD, NEA), and a dermatologist's examination, sometimes with a skin scraping or a biopsy, settles the question (DermNet, BAD).
| Condition | How it differs from nummular eczema |
|---|---|
| Ringworm (tinea corporis) | A fungal infection that starts as a single round red patch with a raised, scaly leading edge and spreads outwards, clearing in the centre; the pattern is typically asymmetrical and it is contagious. Skin scrapings show the fungus (DermNet, NHS). Ringworm treated with a steroid cream loses its typical features (tinea incognito) and becomes harder to recognise (DermNet). |
| Plaque psoriasis | Dry, itchy, sore patches with thick silvery-white scale, typically on the scalp, elbows, knees, trunk and lower back, often with a symmetrical pattern; nail pitting may be present (NHS). |
| Pityriasis rosea | A single larger "herald patch" on the chest, abdomen or back, followed about two weeks later by smaller oval scaly patches along the skin lines of the trunk in a Christmas-tree pattern; it clears on its own in 6 to 10 weeks (DermNet). |
| Contact dermatitis | Itchy, blistered, dry and cracked skin in the area that touched an irritant or allergen, typically the hands or face, within hours or days of contact; the shape follows the contact (NHS, DermNet). |
| Atopic eczema | Itchy, dry, cracked or thickened skin in the elbow and knee creases, on the hands and, in babies, the face; usually starts in early childhood and often runs in families (NHS). Discoid patches can occur within atopic eczema (DermNet). |
| Asteatotic eczema (eczema craquelé) | Very dry skin, mostly on the shins of older people, with a "crazy-paving" pattern of diamond-shaped plates separated by red cracks rather than discrete coins (DermNet). |
| Venous (stasis) eczema | Itchy, red, scaly or crusted plaques on one or both lower legs with swelling, varicose veins and orange-brown staining of the skin; discoid eczema on the legs can be related to it (DermNet). |
| Lichen simplex (neurodermatitis) | One or a few thickened, leathery, well-defined plaques with exaggerated skin markings, produced by long-term scratching; neck, wrists, forearms, ankles and shins (DermNet). |
| Granuloma annulare | Smooth, skin-coloured or red rings over the knuckles, hands, feet or elbows, with a slightly depressed centre, smooth without scale and usually without symptoms; mostly children, teenagers and young adults (DermNet). |
| Bowen's disease (squamous cell carcinoma in situ) | One or more persistent, irregular, scaly orange-red or brown plaques, most often on sun-damaged skin of the ears, face, hands or lower legs, with an asymmetrical distribution; a biopsy confirms it (DermNet). |
| Mycosis fungoides | A rare skin lymphoma: poorly defined, finely scaling, slowly changing patches on sun-protected skin such as the lower trunk, thighs and breasts, progressing over years; often itchy before it is visible (DermNet). |
| Impetigo | A contagious bacterial infection with pustules and honey-coloured crusted erosions, most often on the face; it can also infect an eczema patch (DermNet). |
When to see a doctor
- See a pharmacist or GP (family doctor) if you think you may have nummular eczema; a pharmacist can recommend a suitable treatment, and a GP can refer you to a dermatologist if the diagnosis is unclear or you need a patch test (NHS).
- See a GP if the eczema does not improve after using an over-the-counter emollient or mild treatment (NHS), if the patches keep returning, or if the itch is disturbing your sleep.
- Get medical advice promptly if the patches look infected: a lot of oozing, a yellow crust, hot, swollen or painful surrounding skin, or fever and feeling unwell (NHS, HSE). Infection can spread quickly, and steroid creams can mask or spread it (NHS).
- Same-day care, or the emergency department (A&E) out of hours, for clusters of painful blisters or punched-out sores spreading over the skin with fever and swollen glands, which may be eczema herpeticum (DermNet).
How nummular eczema is diagnosed
In most cases the appearance of the patches is characteristic enough for a GP or dermatologist to make the diagnosis by examining the skin and asking about your history (DermNet, NHS, MedlinePlus). Tests are used to rule out look-alikes and to find a trigger (DermNet, BAD):
- Skin scrapings for fungal microscopy and culture, because nummular eczema can look very like ringworm (DermNet, BAD).
- Bacterial swabs, which may show Staphylococcus aureus colonisation or infection (DermNet, AAD).
- Patch testing for contact allergy, which should be considered in chronic nummular eczema; allergy to nickel and chromate is commonly found (DermNet). In studies, between 33% and 50% of people whose nummular eczema failed to improve with treatment turned out to have a contact allergy, and finding and treating the allergy helps some people get rid of the eczema (AAD). Patch tests are applied to the back for 48 hours and read at 96 hours (DermNet).
- A skin biopsy, a small sample examined under the microscope, when the picture is unusual or another condition is suspected (BAD, AAD, MedlinePlus).
- Attention to the leg veins when patches keep recurring on the lower legs, because varicose veins and venous eczema can underlie discoid eczema there and make its distribution asymmetrical (DermNet).
A dermatologist can often make a provisional assessment from good photographs and a description of the history; scrapings, swabs, patch tests and biopsies are done in person.
Treatment
There is no simple cure, but treatment eases the symptoms and keeps the condition under control (NHS). The plan combines restoring the skin barrier, calming the inflammation, treating infection and removing triggers (NHS, DermNet, AAD).
- Emollients, all the time. Moisturising treatments reduce water loss and cover the skin with a protective film; use them even when there are no symptoms, because they help prevent the eczema returning (NHS). Apply a large amount, smooth it on in the direction of hair growth rather than rubbing, reapply every 2 to 3 hours for very dry skin, and always within minutes of a bath or shower while the skin is still moist (NHS, AAD). A fragrance-free cream or ointment holds water in the skin better than a lotion (AAD); ointments suit very dry skin that is not inflamed, while lighter creams and lotions are more suitable for inflamed areas (NHS). Keep using the emollient on the unaffected skin too, and long after the patches have cleared (DermNet, BAD).
- Soap substitutes. Replace soaps, liquid soaps, bubble bath, shower gels and wet wipes with an emollient wash, even if they do not obviously irritate your skin (NHS).
- Topical steroid for flare-ups. A steroid cream or ointment prescribed by a doctor reduces the inflammation. Nummular eczema usually needs a stronger steroid than other types of eczema (NHS); mild preparations are not usually strong enough, and the mainstay is a potent or very potent one applied to the patches only, avoiding the surrounding normal skin, until the redness and swelling subside, then restarted at the first sign of recurrence (BAD). DermNet gives a typical course as once or twice daily for 2 to 4 weeks; a steroid-impregnated tape is an alternative for thick patches (DermNet). Applying the treatment to damp skin straight after bathing helps it work (AAD). Leave 20 to 30 minutes between the emollient and the steroid, and ask which to apply first (NHS).
- Non-steroid immune-calming creams. Prescribed creams or ointments that calm the immune response in the skin can be used instead of or alongside steroids, for example on sensitive areas or for longer-term control (BAD, MedlinePlus).
- Antibiotics when the patches are blistered, sticky, crusted or clearly infected, as a combined cream or as tablets; nummular eczema sometimes clears completely on an antibiotic course only to recur when it is stopped (DermNet, NHS).
- Antihistamines for severe itch. They do not clear the rash, but a sedating antihistamine at night can help you sleep, and being well rested helps the skin heal (NHS, DermNet, AAD).
- Wet wraps. For acute, weeping or intensely itchy patches, wet bandages over emollient or the prescribed cream cool the skin and improve absorption; they also protect the skin from the itch-scratch cycle and are used for a few days under a doctor's instruction (DermNet, MedlinePlus).
- Phototherapy. Ultraviolet light treatment several times a week for 6 to 12 weeks can reduce itch and improve widespread nummular eczema (DermNet, AAD).
- Treatments for severe or stubborn disease, all prescribed and monitored by a dermatologist: a steroid injection into one or two particularly stubborn patches (DermNet), a short course of steroid tablets, which is rarely needed (DermNet, BAD), immune-suppressing tablets that require careful monitoring (DermNet, BAD), and newer targeted injectable or tablet treatments that a specialist may consider (BAD).
- Treat what is driving it. If patch testing identifies a contact allergy, the allergen should be avoided, and finding and treating an allergy helps some people get rid of the eczema (DermNet, AAD); if venous eczema is involved, treating the leg swelling with elevation and compression is part of the plan (DermNet).
Once treatment starts to work, the dermatologist may adjust it to reduce side effects while keeping the skin clear; if a treatment fails, go back to the dermatologist: a different treatment may be needed, or an undiagnosed allergy may be driving the eczema (AAD).
Self-care and prevention
There is no known way to prevent nummular eczema from occurring in the first place (MedlinePlus), but daily skin care reduces flare-ups and makes treatment work better (AAD, NHS):
- Moisturise every day, all year round, with a fragrance-free, hypoallergenic cream or ointment, on damp skin after every bath, shower and hand wash (AAD).
- Bathe or shower daily in lukewarm, not hot, water, for no longer than 20 minutes, using an emollient instead of soap; pat dry and apply treatments straight afterwards (NHS, AAD).
- Choose "fragrance-free" rather than "unscented" products: unscented products still contain fragrance to mask other smells, and fragrance can irritate the skin even when you cannot smell it (AAD).
- Protect the skin from injury and harsh chemicals: wear gloves with cotton liners for washing up, cleaning and gardening, and wear gloves to avoid cuts, because minor injuries can trigger patches (NHS, DermNet, AAD). Take rings off before washing your hands and moisturise before putting them back (AAD).
- Do not scratch; keep your nails short and your hands clean to limit skin damage and infection (NHS).
- Keep the air moist with a humidifier when indoor air is dry, and avoid overheating: sitting next to a heater or fire, and sweating, can set off a flare (AAD).
- Wear loose clothing of soft, breathable fabric such as cotton; wool, polyester, nylon and other rough or tight fabrics can trigger a flare (AAD, MedlinePlus).
- Reduce stress where you can, and if you drink alcohol, drink in moderation, because heavy drinking is a recognised trigger (AAD).
- Keep a short note of new products, activities and flare-ups to spot your own triggers, and check the ingredients of cosmetics and toiletries that touch your skin (NHS).
Outlook
Nummular eczema is a long-term condition that tends to relapse in winter, but with treatment it can clear completely and, over the years, many cases do eventually resolve (DermNet, AAD). Consistent self-care means fewer new flare-ups (AAD); the emollient continues after the patches have cleared, and the prescribed treatment is restarted at the first sign of a new patch (BAD).
Online dermatologist consultation
If you have round, itchy patches that are not settling, you can book an online consultation with an iDerma dermatologist. Send clear photographs of the patches, close up and from further away, and describe when they started, whether they ooze or crust, what seems to trigger them and what you have already tried. The dermatologist will assess whether the picture fits nummular eczema or one of its look-alikes and will recommend a treatment plan or further tests. Prescription treatments are arranged according to the rules of your country, and scrapings, patch tests or a biopsy, when needed, are done in person.
What to do now
- Start an emollient routine today: a fragrance-free cream or ointment several times a day and straight after washing, with an emollient instead of soap (NHS, AAD).
- If the patches are red, weeping or very itchy, see a pharmacist for advice, or a GP or dermatologist for a prescribed anti-inflammatory treatment; nummular eczema usually needs a stronger steroid than other eczemas, so an over-the-counter mild cream is often not enough (NHS, BAD).
- Seek prompt care for signs of infection, and same-day care for spreading clusters of painful blisters with fever (NHS, DermNet).