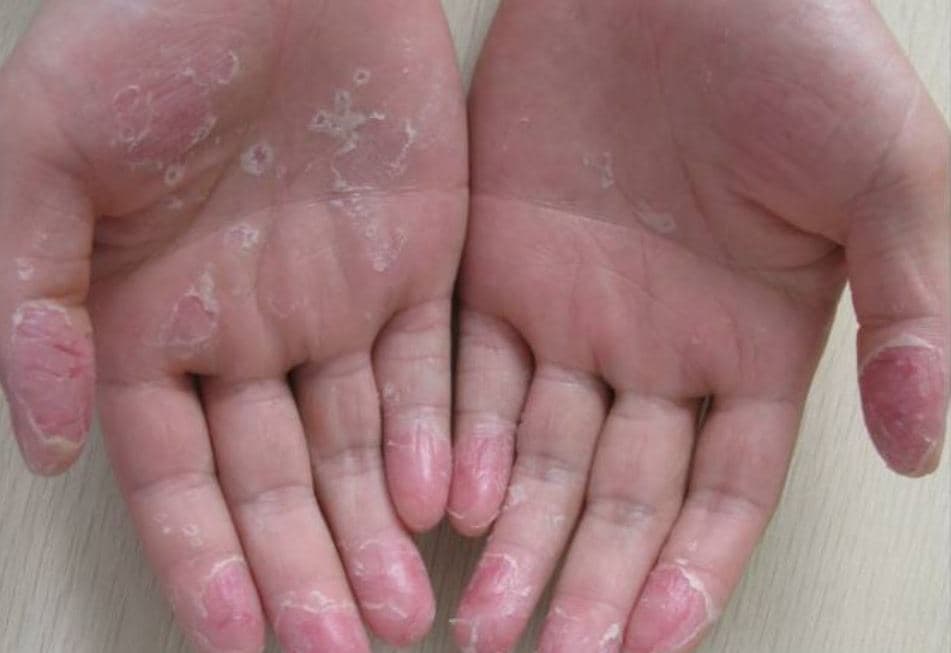
Peeling of the palms, small blisters, cracking, and roughness are common problems that cause concern and lead people to seek help. One of the common but not always correctly identified conditions is exfoliative keratolysis. Although the name sounds scientific, the condition itself is usually harmless but can be bothersome, recurrent, and interfere with daily activities. The key is to understand what it is, how to distinguish it from other skin conditions, what care is most effective, and when it is worth consulting a specialist.
Exfoliative keratolysis is more often observed in warmer seasons and most commonly affects the palms and fingers, less frequently the soles. The condition is not contagious, not related to poor hygiene, and can equally affect men and women, adults, and adolescents. With proper skin care, flare-ups can be significantly reduced, and in many cases, the skin regenerates on its own once irritants are removed.
What is it?
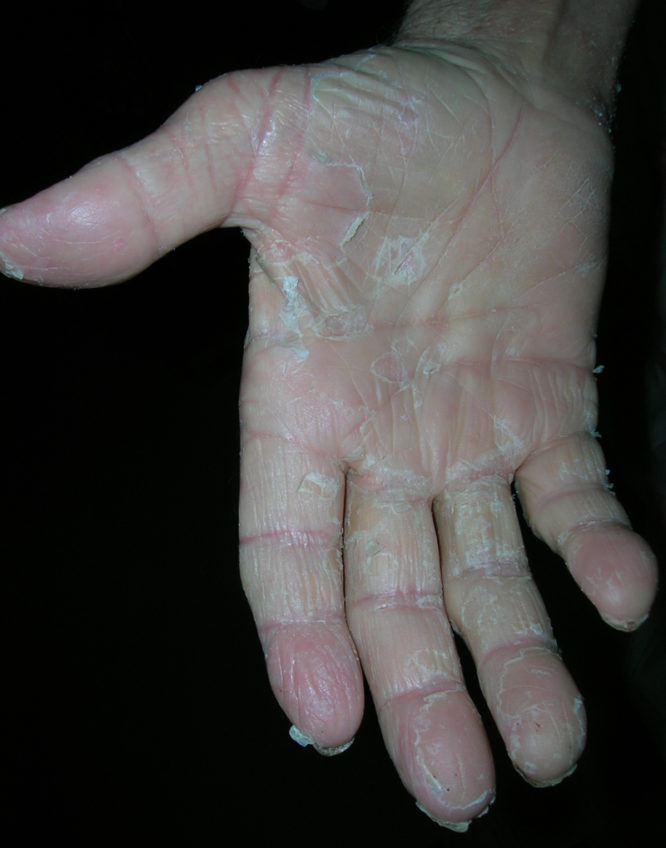
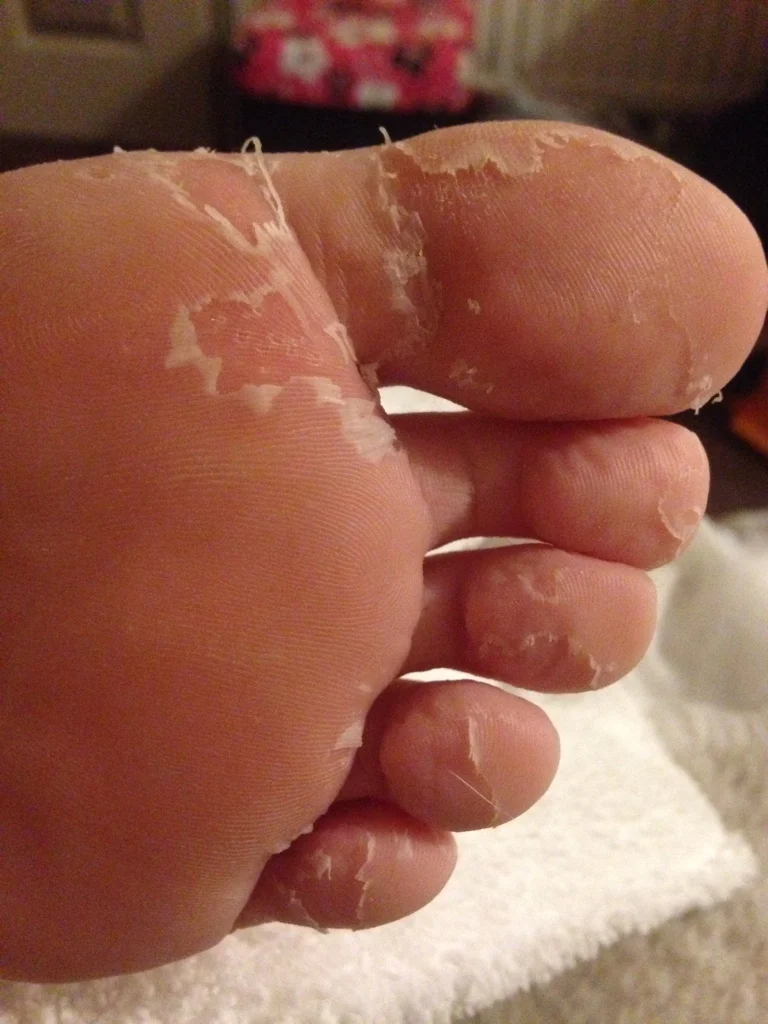
Exfoliative keratolysis is the superficial peeling of the skin's horny layer (stratum corneum). Initially, small, air-filled blisters or thin "pockets" appear, which later burst and leave clearly visible, round or oval peeling areas. Under the peeled surface, a smoother, pinker, more sensitive skin layer is visible. The condition is essentially related to changes in the skin's "adhesion" mechanism (desmosomes) at the junctions of the horny layer cells, making the surface cells detach more easily.
It is very important to know that this is not an infection and usually not an allergy. The condition can be triggered by external factors such as frequent hand washing with harsh cleansers, solvents, friction, sweating, and heat. For these reasons, exfoliative keratolysis is often confused with irritant or allergic dermatitis, fungal infections, or so-called "water eczema" (pompholyx), but these are different conditions requiring different care.
Causes and Risk Factors
The exact cause of exfoliative keratolysis is still not fully understood, but several important factors clearly emerge:
- Chemical irritants and cleansers – harsh soaps, detergents, solvents, disinfectants can damage the skin's protective barrier, disrupt natural lipids, and irritate the horny layer.
- Frequent hand contact with water – so-called "wet work" (frequent washing, soaking) softens the skin, and when it dries, the surface layers are more easily "lifted" and peel off.
- Heat and sweating – palmar hyperhidrosis (excessive sweating) and warmer seasons are associated with more frequent flare-ups.
- Friction and mechanical irritation – sports, working with tools, intensive use of keyboards or instruments.
- Individual sensitivity – some people have naturally more sensitive skin, and family history (genetic predisposition) may play a role.
- Occupational factors – healthcare, beauty, cleaning, food production, metalworking fields where frequent contact with water and chemicals occurs.
The combination of these factors weakens the skin barrier and increases the likelihood that horny cells will detach as flakes. Removing or reducing the impact of irritants usually reduces flare-ups.
Symptoms
Exfoliative keratolysis most often occurs on the palms and sides of the fingers. Typical signs:
- Small, air-filled blisters or vesicles that often burst painlessly.
- Peeling "rings" – clearly defined, round or oval peeling areas.
- Pinker, smoother, sometimes sensitive skin under the peeled area.
- Minimal itching or none – itching is not typical, but a sensation of tightness or roughness may occur.
- Seasonal nature – about half of the cases worsen in warmer seasons.
- Tendency to recur – episodes may recur every few weeks or months.
Unlike irritant or allergic dermatitis, exfoliative keratolysis lesions are usually not brightly red, weeping, and less itchy. Compared to fungal infections, the affected areas are more often on the palms (not just the feet), without characteristic "ring" shaped red edges or a specific odor.
When to See a Doctor?
In milder cases, self-care may be sufficient. However, it is recommended to consult a dermatologist if:
- you are unsure of the diagnosis or the rash does not resolve within 4–6 weeks despite avoiding irritants and proper moisturizing;
- there is pain, bleeding cracks, pus, swelling or fever;
- rashes spread to the feet, nails, or nail changes occur;
- the condition interferes with work or daily activities;
- a child or adolescent is affected, and the condition recurs;
- you suspect occupational irritants and need work environment adaptation advice.
Our iDerma clinic dermatologists help accurately diagnose, assess severity, and develop an individualized treatment and care plan. Consultations are available both in person and remotely, allowing for quick answers and safe initiation of the most appropriate care.
Diagnosis
Exfoliative keratolysis is most often diagnosed clinically – by evaluating the typical appearance and location. A detailed history is important for the dermatologist: what products you use to wash your hands, whether you often wear gloves, work with chemicals, whether your palms sweat heavily, or if you have noticed seasonality.
If the clinical picture is unusual or other conditions are suspected, additional tests may be performed:
- Microscopic fungal tests and cultures – help rule out fungal infections.
- Patch tests (allergy tests) – if contact allergic dermatitis is suspected.
- Dermatoscopic evaluation – helps to see surface skin changes more clearly.
- Skin biopsy – rarely performed when the diagnosis remains unclear.
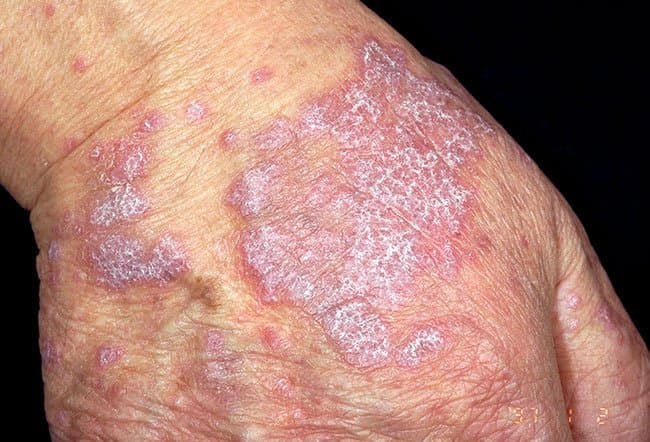
Differential diagnoses: irritant or allergic hand dermatitis, fungal infections, pompholyx (vesicular eczema), palmoplantar psoriasis, as well as some bacterial foot conditions. Correct differentiation is important as care and treatment strategies differ.
Treatment
The goals of treatment are to restore the skin barrier, reduce the impact of irritants, and control flare-ups. Often, consistent, targeted skin care and lifestyle changes are sufficient.
- Identifying and avoiding irritants – limit the use of strong cleansers, solvents, harsh disinfectants. If unavoidable, be sure to use appropriate protective measures.
- Gentle cleansing – choose milder cleansers that do not disrupt the skin barrier. Wash with lukewarm, not hot water, and thoroughly rinse off product residues.
- Regular moisturizing – emollients are applied several times a day, especially after each hand wash and before bedtime. Look for products that restore the barrier and help "lock" moisture in the skin; beneficial formulations may contain components that gently soften the horny layer and strengthen the protective film (e.g., urea, lactic acid, silicone, or similar moisturizers and barrier ingredients).
- Night protection – before bed, apply a generous amount of emollient and wear thin, clean cotton gloves. This increases the effectiveness of the product and reduces friction during the night.
- Smart glove use – when working with water or chemicals, wear protective gloves. Underneath, wear thin cotton liner gloves to reduce sweating and friction. Avoid prolonged continuous wear – allow the skin to "breathe."
- Sweating control – if palms sweat heavily, discuss with a dermatologist measures to reduce sweating. Targeted sweat management often significantly reduces the frequency of flare-ups.
- Phototherapy or procedural solutions – for persistent or frequently recurring cases, a dermatologist may recommend office procedures such as selective light therapy or other instrumental methods.
Unlike other inflammatory hand skin conditions, exfoliative keratolysis often responds poorly to conventional anti-inflammatory ointments. Therefore, a correct diagnosis is especially important – it helps choose the most effective, safe strategy and avoid unnecessary, unhelpful treatment.
iDerma dermatologists, after assessing your skin, work and leisure habits, and the range of irritants, create an individual plan: from daily care steps to office procedures. We can consult both in person and online – it is convenient and fast, and recommendations are tailored to your real situations.
Care and Prevention
To reduce the frequency and intensity of flare-ups, consistent daily care and prevention are important. Practical tips:
- Create a "hand care ritual": in the morning – moisturizing cream after washing; during the day – reapplication after each wash; in the evening – a thicker layer of emollient and, if needed, cotton gloves for the night.
- Wash hands only when necessary – in some cases, washing can be replaced with gentle wipes or a brief rinse with lukewarm water without intense rubbing.
- Avoid hot water – high temperatures more strongly disrupt the lipid barrier and promote dryness.
- Choose disinfectants carefully – if you must use them, always apply a moisturizer afterward. Look for milder, less drying formulations.
- Use gloves wisely – for washing and cleaning, choose protective ones, but avoid prolonged continuous wear. After work, dry your hands and immediately apply a moisturizer.
- Reduce friction – if you work with tools or engage in sports, use pads, inserts, or gloves that reduce mechanical irritation.
- Care for microcracks – as soon as you feel tightness or roughness, apply a generous amount of emollient; small cracks heal faster if not allowed to deepen.
- Have a "travel" moisturizer – keep a small package at your workplace, in the car, or in your bag for frequent and convenient application.
If flare-ups recur despite thorough prevention, it is worth reviewing habits with a dermatologist: sometimes the cause lies in less obvious factors (e.g., specific cleaning products at work, glove material, a habit of washing hands with very hot water or prolonged soaking in a sauna, pool).